


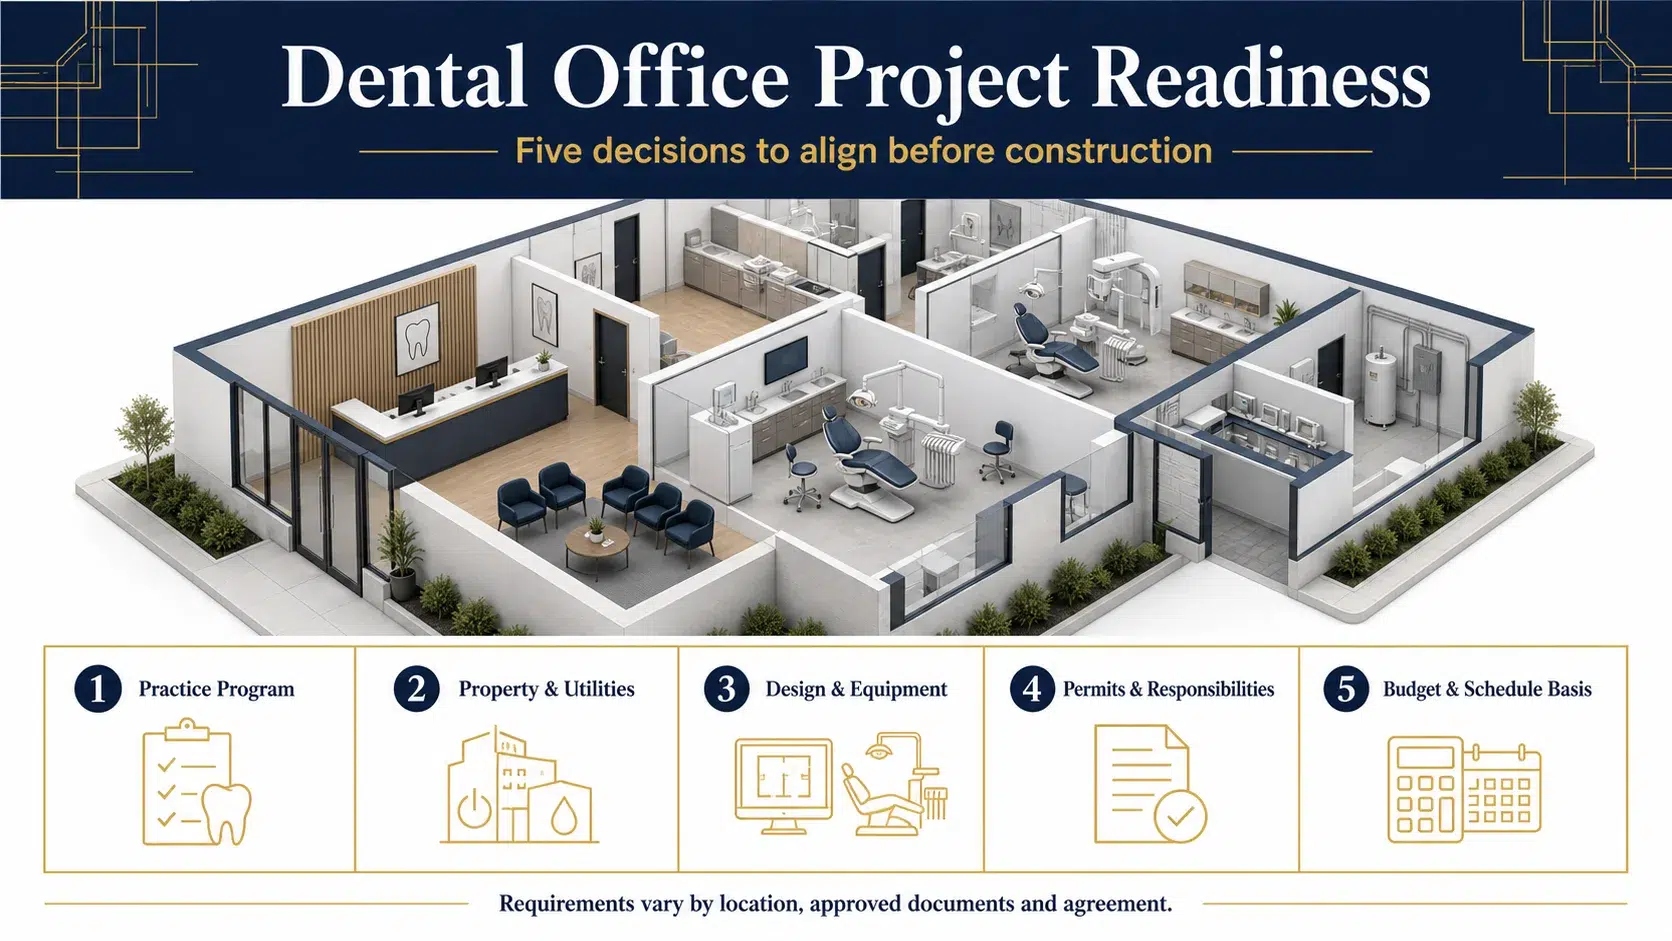
Dental office construction succeeds or fails on decisions made before demolition begins. The property must support the intended practice, selected equipment must be coordinated with the building systems, responsibilities must be documented, and the budget and schedule must follow the actual scope—not a generic national average.
In 2024, about 34% of U.S. dentists worked in solo practices, and California had the highest state share at 44%, according to the American Dental Association Health Policy Institute’s U.S. Dentist Workforce 2025 report. For an owner-dentist, that makes the physical practice an important operating decision as well as a construction project.
This guide explains the owner decisions that shape a Bay Area dental office build-out—from pre-lease feasibility and equipment coordination to permits, budget, construction and handover. Requirements vary by practice type, property, jurisdiction, approved documents and contract.
What Is Dental Office Construction?
Dental office construction is the planning and construction of a clinical space around the practice program, treatment equipment, staff and patient circulation, support functions and applicable approvals. Unlike a general office renovation, a dental build-out can require tightly coordinated plumbing, vacuum and compressed-air systems, imaging criteria, electrical and data capacity, sterilization workflow, accessibility, acoustics and infection-control finishes.
The exact requirements are not universal. A general practice, orthodontic clinic, pediatric practice and oral-surgery office can have very different room relationships, equipment loads, privacy needs and vendor responsibilities. The approved program and equipment schedule should drive the design—not a generic floorplan copied from another practice.
Choose the Project Path Before Choosing the Layout
| Project path | Early decision | Common coordination risk |
|---|---|---|
| New practice or relocation | Test the property before lease commitments become difficult to change. | Use, utility capacity, accessibility, landlord work and equipment lead times. |
| Remodel in an operating clinic | Define phasing, infection-control boundaries and shutdown windows. | Patient/staff separation, noise, dust, temporary services and lost production time. |
| Expansion | Verify that existing systems can support the added program. | Panel, HVAC, vacuum, compressor, plumbing, data and egress capacity. |
| Specialty conversion | Confirm specialty equipment, clinical criteria and professional responsibilities. | Imaging, shielding, sedation or medical-gas scope, privacy and recovery requirements where applicable. |
| Ground-up facility | Integrate site, shell and clinical decisions into one development basis. | Entitlements, utilities, civil work, shell systems and a longer approval/procurement chain. |
Before You Sign a Lease: Dental Property Feasibility
A visually attractive space is not necessarily a feasible dental office. Pre-lease due diligence should test the intended use and clinical program against the property before the owner relies on a construction budget or opening date.
Pre-Lease Feasibility Checklist
- Permitted use: Confirm that the intended dental use is allowed and identify any change-of-use or occupancy implications.
- Landlord scope: Document base-building work, delivery condition, utility points, roof access, penetrations, restoration obligations and approval procedures.
- Electrical service: Compare available service, panels and pathways with the preliminary equipment and technology loads.
- Mechanical capacity: Test HVAC capacity, zoning, ventilation, equipment heat rejection and the location of compressor/vacuum equipment.
- Plumbing and wastewater: Review routing, slab conditions, drainage, venting and the feasibility of chair, sterilization and equipment connections.
- Imaging: Identify proposed equipment early so the qualified team can establish power, data, structural and shielding criteria where applicable.
- Accessibility and circulation: Review the route from site arrival through reception, treatment and accessible support spaces.
- Existing conditions: Decide what must be surveyed, opened, tested or verified before design and pricing assumptions harden.
- Schedule constraints: Record lease dates, landlord review, design, permits, long-lead equipment, construction, inspections and vendor commissioning.
A lease contingency or formal feasibility period should be discussed with the owner’s broker, attorney and project advisers. A preliminary contractor walk-through is useful, but it does not replace architectural, engineering, clinical, legal or agency review.
Build a Defensible Dental Office Budget
Published dental-industry benchmarks such as the Dental Clinic Manual and current business-planning guides can identify categories, but they are not Bay Area bids. A reliable budget becomes more precise as the property, equipment, drawings and responsibility boundaries become more precise.
| Budget account | What to define | Typical owner question |
|---|---|---|
| Landlord/base building | Delivery condition, service upgrades, penetrations, roof and common-area work. | What is included in the lease, and what becomes tenant work? |
| Construction | Demolition, framing, finishes, MEP, low-voltage pathways and contractor general conditions. | Which drawings and assumptions support the estimate? |
| Professional services | Architecture, engineering, specialty consultants, surveys and testing. | Who designs each system and seals required documents? |
| Dental equipment and technology | Chairs, delivery units, imaging, sterilization, compressor/vacuum, IT and security. | Who purchases, installs, connects, tests and trains? |
| Permits and agency costs | Plan review, permits, inspections, utility or specialty submissions. | Which fees are included, allowances or owner-direct? |
| Owner-provided scope | Furniture, signage, moving, supplies, temporary operations and opening activities. | What sits outside the construction contract? |
| Risk and escalation | Existing-condition uncertainty, design development, procurement timing and owner contingency. | Who controls each reserve and when may it be used? |
Do not compare estimates by bottom-line price alone. Normalize exclusions, allowances, taxes, fees, equipment connections, landlord work, design maturity and schedule assumptions before treating two numbers as comparable.
Dental Office Design: Workflow Before Aesthetics
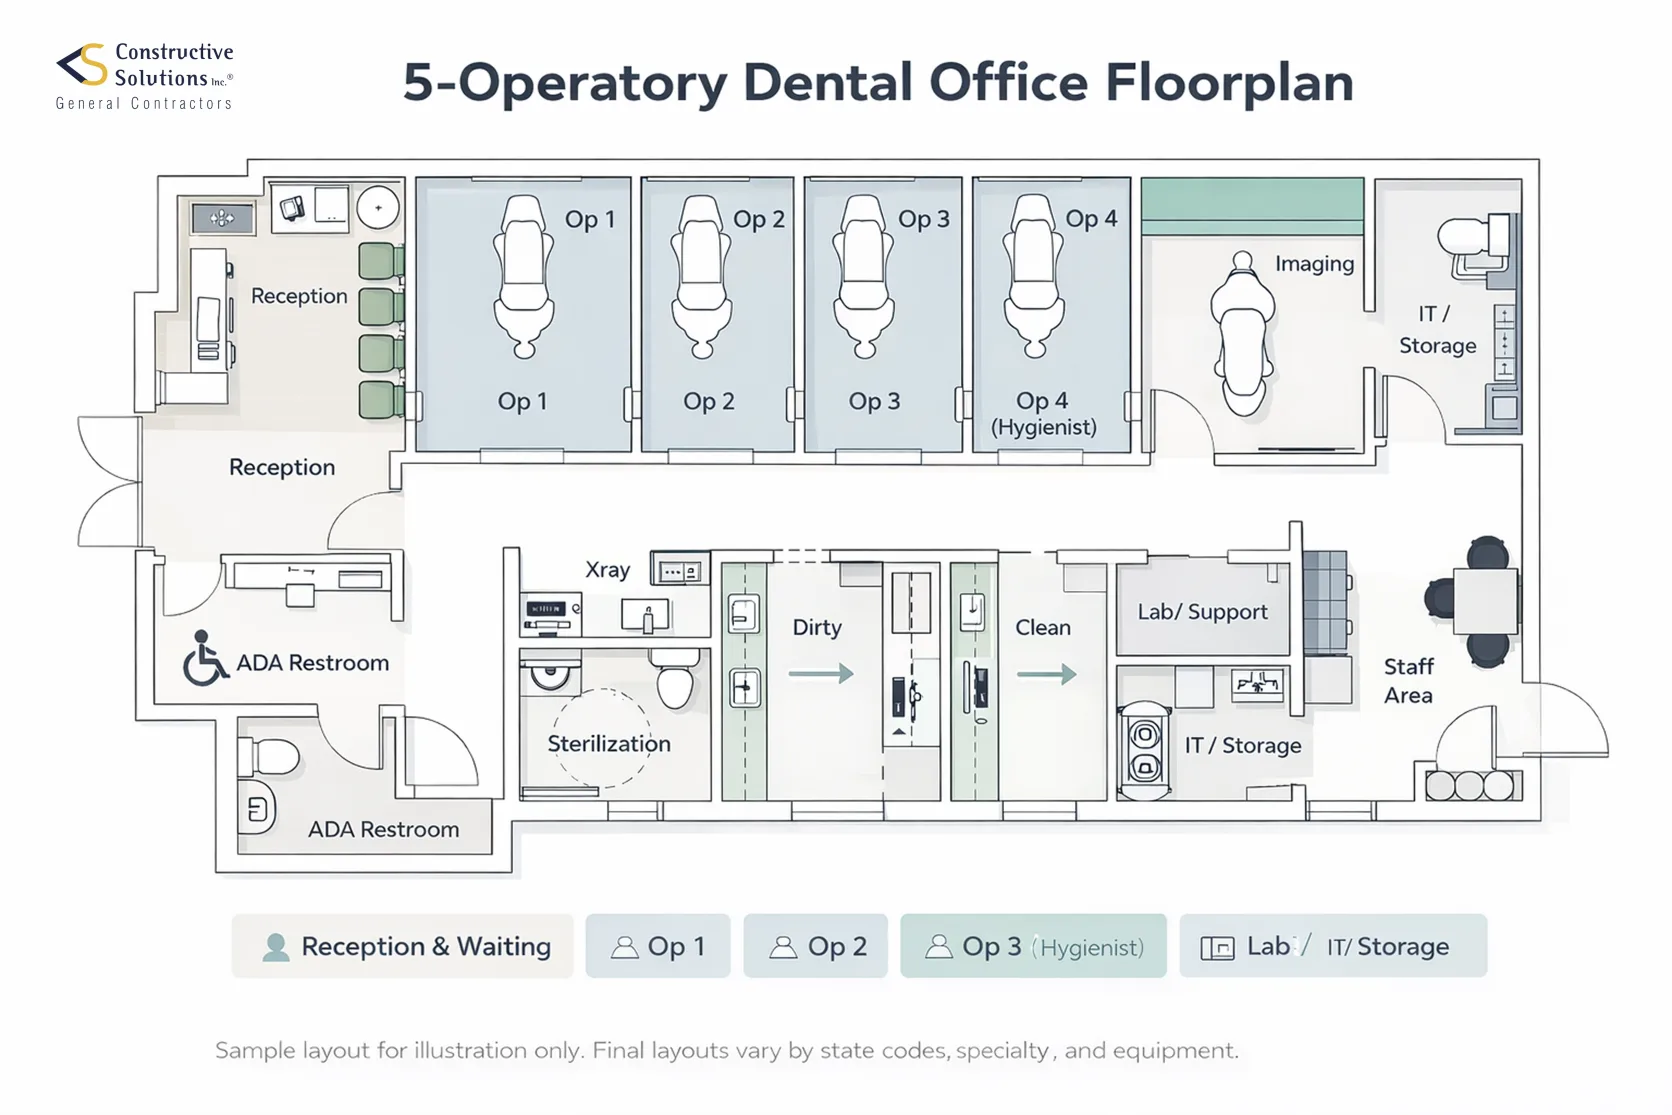
Space planning should begin with the practice program: provider count, treatment types, staffing, equipment, support functions, patient flow and realistic expansion. The selected equipment—not a generic room dimension—should establish clearances and connection requirements.
Workflow Questions to Resolve
- How do patients, staff, instruments, supplies and waste move through the clinic?
- Which functions need visual connection, acoustic separation or controlled access?
- Where will clean and contaminated instrument paths be established by the practice and clinical advisers?
- What equipment clearances, service zones and maintenance access must remain available?
- Which rooms need privacy, shielding, specialty ventilation or structural review?
- How will deliveries, storage, IT, staff support and future changes be accommodated?
Accessibility and patient-information privacy involve different requirements and professional responsibilities. A layout alone does not establish ADA or HIPAA compliance. Those criteria should be interpreted by the owner’s qualified advisers and incorporated into approved documents.
Assign Dental Project Responsibilities Before Design Is Final
Many dental construction problems are interface problems: an equipment vendor assumes the electrician will provide a connection, the electrician expects a final cut sheet, or the owner believes a landlord upgrade is included. A written responsibility matrix makes those assumptions visible while they can still be resolved.
| Participant | Questions to document | Required handoff |
|---|---|---|
| Owner/dentist | Practice program, equipment decisions, clinical criteria, budget authority and operating constraints. | Approved program, timely decisions and identified owner vendors. |
| Architect and engineers | Code analysis, planning, system design, equipment criteria and permit documents. | Coordinated, approved documents and responses to field questions. |
| Dental equipment vendor | Final models, layouts, connection points, loads, backing, delivery and commissioning. | Current cut sheets, shop drawings and installation/commissioning plan. |
| IT, imaging and specialty vendors | Power, data, pathways, heat, security, shielding criteria and testing. | Coordinated requirements before rough-in and enclosure. |
| Contractor | Pricing basis, constructability, logistics, procurement, sequencing, RFIs, changes and closeout. | Work performed to the agreed scope and approved documents. |
| Landlord/base-building team | Review procedures, building rules, shutdowns, roof/shaft work and service upgrades. | Written approvals and delivery of committed landlord work. |
| Authorities and utilities | Submittals, reviews, inspections, registration and service requirements. | Required approvals; no project participant should promise an agency outcome. |
Dental Equipment and Building-System Coordination
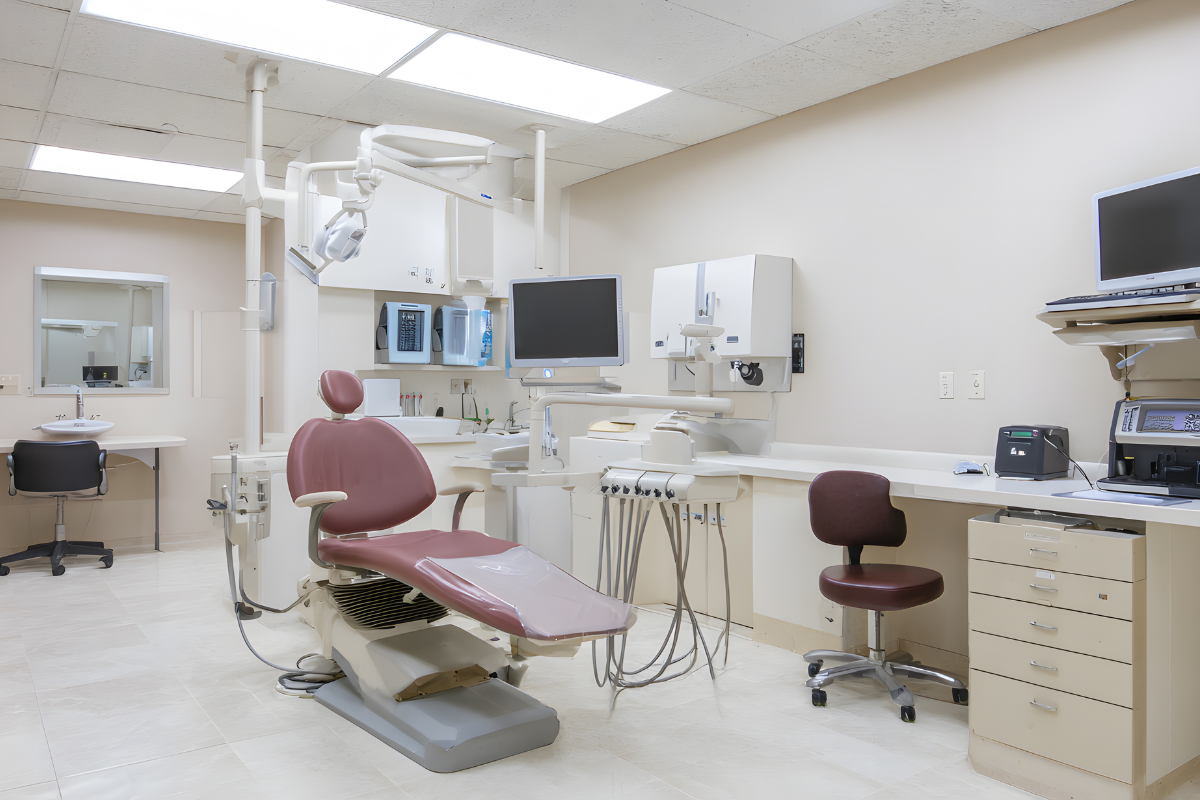
Dental equipment should be selected early enough for the design team to confirm loads, clearances, connection points, drainage, heat rejection, data needs, support and shielding criteria where applicable. The contractor should receive coordinated requirements before rough-in work is concealed.
Systems That Commonly Need Coordination
- Water, waste and suction: chair locations, traps, vents, slab or wall routing, cleanouts and service access.
- Compressed air and vacuum: selected equipment, central-unit location, intake/exhaust, acoustics, heat and maintenance access.
- Electrical: actual connected loads, dedicated circuits, emergency requirements where applicable, panels, pathways and future program assumptions approved by the owner and engineers.
- Imaging and technology: power, data, network/security, structural support, room configuration and shielding criteria established by qualified professionals.
- Sterilization and lab support: equipment sequence, sinks, ventilation, millwork, clearances and utility connections.
- Millwork and backing: equipment-vendor dimensions, wall supports, access panels and installation tolerances.
Do not rely on preliminary equipment brochures when final cut sheets are available. Model substitutions can change connection points, loads and clearances after walls, floors or cabinetry have already been designed.
Bay Area Permits and Dental-Specific Compliance Questions
The project team should build an address-specific approval map. Requirements can include planning and building review, accessibility, fire and life safety, structural and equipment loads, plumbing, mechanical, electrical, workplace safety, radiation controls, wastewater obligations and dental-practice rules.
- Local use and building approvals: San Francisco permit materials recognize clinics-medical/dental as a use category, but that does not establish approval for a particular address. Confirm current requirements with the responsible city or county.
- Radiation machines: a California facility that possesses reportable X-ray equipment may need registration with the California Department of Public Health Radiologic Health Branch. The qualified team should establish shielding, installation, survey and operational responsibilities for the selected equipment.
- Dental wastewater: the federal EPA dental-office category rule applies to covered dental offices that place or remove amalgam and discharge amalgam process wastewater. Applicability, separator or equivalent-device requirements, reporting and the responsible local control authority should be confirmed for the practice.
- Accessibility and workplace safety: use current project-specific guidance from the ADA accessibility resource, OSHA, the authority having jurisdiction and qualified professionals.
- Infection control: the practice and clinical advisers should establish criteria using current CDC dental infection-control guidance; construction documents then coordinate the agreed physical requirements.
Contractor coordination is not a guarantee of licensing, certification, code interpretation or regulatory approval. Those responsibilities must be assigned to the appropriate owner, clinical, design, vendor or agency participant.
Dental Office Construction Sequence and Decision Gates
- Define the practice program. Confirm treatment types, providers, staff, operatories, support spaces and growth assumptions.
- Test the property. Review use, utilities, accessibility, landlord scope, existing conditions and major system constraints.
- Select and coordinate equipment. Obtain layouts, final cut sheets, vendor responsibilities and procurement dates.
- Develop coordinated documents. Resolve architecture, engineering, equipment, technology and specialty criteria before pricing and permits are treated as final.
- Align budget and scope. Normalize allowances, exclusions, owner-direct work, alternates and risk reserves.
- Complete reviews and procurement. Track landlord, agency, utility and long-lead decisions as separate schedule dependencies.
- Build and document. Manage logistics, submittals, RFIs, inspections, changes and concealed-condition decisions under the contract process.
- Coordinate vendor installation. Sequence equipment, IT, imaging, furniture and commissioning with construction completion.
- Close out and prepare operations. Complete punch work, applicable inspections, owner training by the responsible vendors, record documents and handover requirements.
There is no universal dental-office duration. A defensible schedule follows the actual property, design completeness, permit path, landlord review, utility work, equipment procurement, construction sequence and owner decision dates.
Design Priorities That Hold Up After Opening Day
Visual style matters, but durable dental-office decisions begin with operations and maintenance. Ask the design team to evaluate:
- Cleanability: finish transitions, joints, access and detailing should follow approved clinical and maintenance criteria.
- Acoustics and privacy: treatment, consultation, reception and staff areas may need different separation strategies.
- Lighting: coordinate clinical task lighting, ambient lighting, glare control, controls and equipment needs instead of relying on color trends alone.
- Wayfinding and accessibility: make arrival, check-in, treatment and accessible support spaces understandable and usable.
- Serviceability: preserve access to valves, filters, controls, IT, equipment and components that require maintenance.
- Adaptability: document realistic future equipment or operatory assumptions before installing unused capacity.
- Brand expression: use materials, color, signage and artwork in ways that do not compromise clinical, acoustic, accessibility or maintenance requirements.
How to Verify a Dental Construction Partner
A visually appealing project is not proof that a contractor can deliver your clinic. Before selection, ask for evidence comparable to the property, scope and delivery role.
- Comparable scope: Confirm whether the firm performed construction, design-build coordination, consulting or another role.
- Permission-safe evidence: Verify project facts, references and images instead of relying on generic portfolio language.
- Responsibility clarity: Identify who owns programming, design, engineering, equipment, permits, landlord work and vendor coordination.
- Project controls: Review how estimates, allowances, schedules, submittals, RFIs, changes, inspections and closeout are documented.
- Licensing and insurance: Verify the requirements that apply to the company and work rather than relying on a logo or marketing claim.
Constructive Solutions publishes its commercial project portfolio so prospective clients can review documented work. Owners should still request project-specific comparable evidence during qualification.
Conclusion
A dental office is a coordinated clinical, operational and construction environment. The strongest projects align the practice program, property, equipment, professional responsibilities, budget and approvals before field work makes changes expensive. That preparation cannot eliminate every existing condition or owner change, but it can make assumptions visible and decisions more defensible.
Discuss Project Fit with Constructive Solutions
Constructive Solutions, Inc. is a San Francisco Bay Area commercial general contractor. We provide preconstruction, design-build and commercial interior build-out services within documented capabilities and an agreed scope. Share the property, practice program, available drawings, equipment plan and target milestones so our team can determine whether the project is a fit. Start a project-fit conversation.
Frequently Asked Questions
How long does dental office construction take?
There is no universal duration. Existing conditions, design completeness, landlord review, permitting, utility work, equipment procurement, inspections and owner decisions all affect the schedule. A defensible duration follows defined scope and approved documents rather than a generic month range.
Can an existing commercial space be converted into a dental clinic?
Potentially. The project team should first confirm permitted use, accessibility, utility capacity, structural and equipment needs, landlord requirements and the feasibility of the approved clinical program.
What size should a dental office be?
Size should follow the number and type of operatories, support spaces, staffing, equipment, circulation, accessibility and realistic expansion needs. A generic national average is not a substitute for programming the intended practice.
How much does dental office construction cost?
No single price per square foot applies. Location, existing conditions, building systems, equipment, design, permits, finish level, schedule and responsibility allocation materially affect cost. Use published benchmarks only for early context and develop the budget from the actual property and scope.
Who installs dental equipment?
Responsibility varies by equipment, vendor agreement and construction contract. The team should identify who purchases, delivers, installs, connects, tests, commissions and trains before rough-in documents are finalized.
What are common dental office construction planning mistakes?
Common risks include selecting a space before testing utilities and use, delaying equipment decisions, unclear responsibility boundaries, incomplete existing-condition information and treating early budgets or schedules as commitments.
Relevant resources:
- Medical and Healthcare Construction
- Commercial Preconstruction Services
- Commercial Interior Build-Out
Constructive Solutions, Inc. is a full-service commercial construction company serving San Francisco and Bay Area.
Whatever your vision, we have the resources, experience, and insight to make your concept a reality, and a space where your business can flourish.
Call Us Now for Estimate









Leave a Reply